1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

EP.1548
Case of cervical tuberculosis presenting as growth
Poster Presenter
Authors
Affiliations
Part of Topic
Benign Gynaecology
- A nulliparous, newly married female of 24.5 yrs presented with complaint of offensive, blood mixed vaginal discharge for a few months, post coital bleeding and intermittent spotting.
- Patient also had complaint of mild dull aching pelvic pain and dyspareunia. Bowel and bladder habits normal.
- Examination suggested a lean built with mild pallor.
- On per speculum examination, cervix revealed friable cervix, bleeds on touch with small papillary growth like lesions.
- No dysmenorrhoea, no heavy bleeding. No significant medical, surgical or family history.
- Patient had history of weight loss and loss of appetite for a few months.
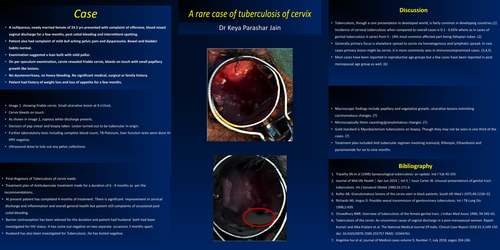
- Image 1. showing friable cervix. Small ulcerative lesion at 9 o’clock.
- Cervix bleeds on touch.
- As shown in image 2, copious white discharge present.
- Decision of pap smear and biopsy taken. Lesion turned out to be tubercular in origin.
- Further labortatory tests including complete blood count, TB Platinum, liver function tests were done.
- Ultrasound done to tule out any pelvic collections.
- Final diagnosis of Tuberculosis of cervix made.
- Treatment plan of Antitubercular treatment made for a duration of 6 - 9 months as per the recommendations.
- At present patient has completed 4 months of treatment. There is significant improvement in cervical discharge and inflammation and overall general health but patient still complaints of occasional post coital bleeding.
- Barrier contraception has been advised for the duration and patient had husband both had been investigated for HIV status. It has come out negative on two separate occasions 3 months apart.
- Husband has also been investigated for Tuberculosis. He has tested negative.
- Discussion
- though a rare presentation in developed world, is fairly common in developing countries.(1) Incidence of cervical tuberculosis when compared to overall cases is 0.1 - 0.65% where as in cases of genital tuberculosis it varies from 5 - 24% most common affected part being fallopian tubes. (2)
- Generally primary focus is elsewhere spread to cervix via hematogenous and lymphatic spread. In rare cases primary lesion might be cervix. it is more commonly sees in immunocompromised cases. (3,4,5)
- Most cases have been reported in reproductive age groups but a few cases have been reported in post menopausal age group as well. (6)
- Macroscopic findings include papillary and vegetative growth, ulcerative lesions mimicking carcinomatous changes. (7)
- Microscopically there casesting/granulomatous changes. (7)
- Gold standard is Mycobacterium tuberculosis on biopsy. Though they may not be seen in one third of the cases. (7)
- Treatment plan included Anti tubercular regimen involving Isoniazid, Rifampin, Ethambutol and pyrazinamide for six to nine months.
BIbliography
Bibliography
1 .TripathySNe tal(1998)Gynaecologicaltuberculosis:anupdate.I n dJ Tub45:193.
2
.JournalofMid-lifeHealth! Apr-Jun2014| Vol5 | IssueCarterJR.Unusualpresentationso fgenitaltract tuberculosis.IntJ GynaecolObstet1990;33:171-6.
3
.KollerAB.Granulomatouslesionsoft h ecervixuteriinblackpatients.SouthAfrMedJ1975;49:1228-32
4
.RichardsMJ,AngusD.Possiblesexualtransmissiono fgenitourinarytuberculosis.I n tJ TBLungDis 1998;2:439.
5
.ChowdhuryN R .Overviewoftuberculosisoft h efemalegenitaltract.J IndianM e dAssoc1996;94:345-61.
6
.Tuberculosisofthecervix:Anuncommoncauseofvaginaldischargeinapost-menopausalwoman.Rajesh KumariandAlkaKriplanie ta l .TheNationalMedicalJournalOfIndia.ClinicalCaseReport2018:31:3;149-150
7
doi:10.4103/0970-258X.255757PMID:31044761.
.