1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

EP.1525
The surgical management of ruptured large dermoid cyst: Open or Laparoscopic.
Poster Presenter
Authors
Affiliations
Part of Topic
Benign Gynaecology
THE SURGICAL MANAGEMENT OF A RUPTURED LARGE DERMOID CYST: OPEN OR LAPAROSCOPIC?
Dr Shehani Alwis MBChB
Dr Veronica R. Powys MBBS
Mr Kostis Nikopoulous MSc PhD MRCOG Consultant Obstetrician and Gynaecologist / Urogynaecologist
Frimley NHSFoundationTrust
OBJECTIVE
The clinical presentation of ovarian dermoid cysts can be variable [1].This case highlights the management of a dermoid cyst rupture.
CASE REPORT
Admission
A 32-year old, nulliparous woman, known to have pedunculated fibroids and a dermoid ovarian cyst, presented to the hospital with acute abdominal pain. The patient reported a history of intermittent pelvic pain and occasional postcoital bleeding.
Initial Investigation
A transvaginal ultrasound scan demonstrated a 47x54mm fluid-filled tubular mass with thickened walls in the left adnexa, with fluid levels of different densities. The ovaries were not visualised and the uterus was difficult to assess due to the presence of a 9 cm fibroid. The patient was diagnosed with a left tubo-ovarian abscess and admitted for intravenous antibiotics.
Clinical Course
The following day the patient deteriorated, developing systemic infective symptoms and significantly raised inflammatory markers compared to baseline. An urgent MRI demonstrated a ruptured ovarian complex cyst, likely dermoid, with significant free fluid in the Pouch of Douglas, abdomen and pelvis. The patient underwent emergency laparoscopy.
Intra-operative findings
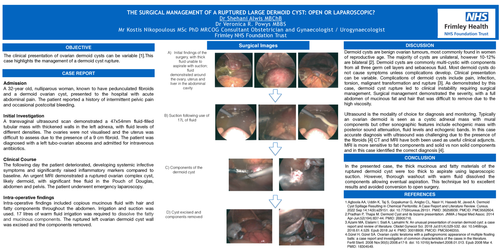
Intra-operative findings included copious mucinous fluid with hair and fatty components throughout the abdomen. Irrigation and suction was used. 17 litres of warm fluid irrigation was required to dissolve the fatty and mucinous components. The ruptured left ovarian dermoid cyst wall was excised and the components removed.
DISCUSSION
Dermoid cysts are benign ovarian tumours, most commonly found in women of reproductive age. The majority of cysts are unilateral, however 10-12% are bilateral [2]. Dermoid cysts are commonly multi-cystic with components from all three germ cell layers and sebaceous fluid. Most dermoid cysts do not cause symptoms unless complications develop. Clinical presentation can be variable. Complications of dermoid cysts include pain, infection, torsion, malignant transformation and rupture [3]. As demonstrated by this case, dermoid cyst rupture led to clinical instability requiring surgical management. Surgical management demonstrated the severity, with a full abdomen of mucinous fat and hair that was difficult to remove due to the high viscosity.
Ultrasound is the modality of choice for diagnosis and monitoring. Typically an ovarian dermoid is seen as a cystic adnexal mass with mural components but other sonographic features include echogenic mass with posterior sound attenuation, fluid levels and echogenic bands. In this case accurate diagnosis with ultrasound was challenging due to the presence of the fibroids [4] CT and MRI have both been used as useful clinical adjuncts. MRI is more sensitive to fat components and solid vs non solid components and in this case identified the correct diagnosis [4].
CONCLUSION
In the presented case, the thick mucinous and fatty materials of the ruptured dermoid cyst were too thick to aspirate using laparoscopic suction. However, thorough washout with warm fluid dissolved the components allowing eventual aspiration. This technique led to excellent results and avoided conversion to open surgery.
REFERENCES
- Agboola AA, Uddin K, Taj S, Gopakumar G, Anigbo CL, Nasir H, Haseeb M, Javed A. Dermoid Cyst Spillage Resulting in Chemical Peritonitis: A Case Report and Literature Review. Cureus. 2022 Sep 14;14(9):e29151. doi: 10.7759/cureus.29151. PMID: 36258939; PMCID: PMC9562604.
- Pradhan P, Thapa M. Dermoid Cyst and its bizarre presentation. JNMA J Nepal Med Assoc. 2014 Apr-Jun;52(194):837-44. PMID: 26905716.
- Azami MA, Elalami I, Siati A, Lamalmi N. An unusual presentation of ovarian dermoid cyst: a case report and review of literature. Obstet Gynecol Sci. 2018 Jul;61(4):529-532. doi: 10.5468/ogs.2018.61.4.529. Epub 2018 Jul 4. PMID: 30018909; PMCID: PMC6046355.
- Gürel H, Gürel SA. Ovarian cystic teratoma with a pathognomonic appearance of multiple floating balls: a case report and investigation of common characteristics of the cases in the literature. Fertil Steril. 2008 Nov;90(5):2008.e17-9. doi: 10.1016/j.fertnstert.2008.01.013. Epub 2008 Mar 4. PMID: 18304549.