1,830 posters, 67 videos, 75 audios, 29 topics, 22 sessions, 4,727 authors, 1,697 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOG World Congress 2023
June 12 - 14, 2023 | London, UK

EP.1090
Postpartum tachycardia and abdominal distension: A case of poorly differentiated Sertoli-Leydig tumour
Poster Presenter
Authors
Affiliations
Part of Topic
Gynae Oncology
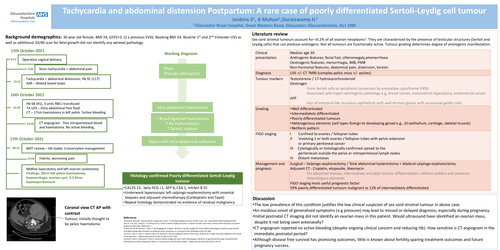
Background demographics: 30 year old female, BMI 34, G5P2+2 (2 x previous SVD). Booking BMI 34. Routine 1st and 2nd trimester USS as well as additional 33/40 scan for fetal growth did not identify any adnexal pathology.
15th October 2021 - 6:13 Operative vaginal delivery, 9:30 Sinus tachycardia and abdominal pain, 15:15 Tachycardia and abdominal distension, Hb 91, AXR dilated bowel loops
16th October 2021 - 13:30 Hb 68, 3 units RBCs transfused, TA USS intra-abdominal free fluid, CT 17cm haematoma in left pelvis, 23 45 CT angiogram free intra-peritoneal blood and haematoma, no active bleeding
17th October 2021 - 00:15 MDT review, Hb stable, conservative management, 12:00 Febrile, worsening pain, Midline laparotomy and left ovarian cystectomy, intra-operative findings 20cm left pelvic haematoma, haemorrhagic cyst, 3.3 litres haemoperitoneum
Histology confirmed Poorly differentiated Sertoli-Leydig tumour.
Literature review
Sex cord stromal tumours account for <0.2% of all ovarian neoplasms1. They are characterised by the presence of testicular structures (Sertoli and Leydig cells) that can produce androgens. Not all tumours are functionally active. Tumour grading determines degree of androgenic manifestation.
Clinical presentation - Median age 30, androgenic features; facial hair, clitoromegaly,amenorrhoea, oestrogenic features; menorrhagia, IMB, PMB, non-hormonal features; abdominal pain, distension, torsion
Diagnosis - USS +/- CT ?MRI (complex pelvic mass +/- ascites)
Tumour markers - Testosterone / 17-hydroxycorticosteroid, Oestrogen (from Sertoli cells or peripheral conversion by aromatase cytochrome P450, associated with hyper-oestrogenic pathology e.g, breast cancer, endometrial hyperplasia, endometrial cancer), AFP (foci of intestinal like mucinous epithelium with well-formed glands with occasional goblet cells)
Grading -
I Confined to ovaries / fallopian tubes
II Involving 1 or both ovaries / fallopian tubes with pelvic extension
or primary peritoneal cancer
III Cytologically or histologically confirmed spread to the
peritoneum outside the pelvis or retroperitoneal lymph nodes
IV Distant metastases
Management and prognosis - Surgical – Salpingo-oophorectomy / Total abdominal hysterectomy + bilateral salpingo-oophorectomy, Adjuvant CT - Cisplatin, etoposide, bleomycin, For advanced disease, intermediate and poor tumour differentiation, retiform pattern and presence heterologous elements. FIGO staging most useful prognostic factor. 59% poorly differentiated tumours malignant vs 11% of intermediately differentiated.
Discussion