296 posters, 7 videos, 13 audios, 14 topics, 10 sessions, 1,019 authors, 260 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
RCOphth Annual Congress 2026
18 - 21 May, 2026 | Manchester Central, Manchester

P285
Relentless placoid chorioretinitis: Case series and review of therapeutic strategies
Poster Presenter
Authors
Chung Shen Chean, Samreen Khanam, Francesca Simonini, Periyasamy Kumar, Bharat Kapoor
Affiliations
Part of Topic
Uveitis
Introduction:
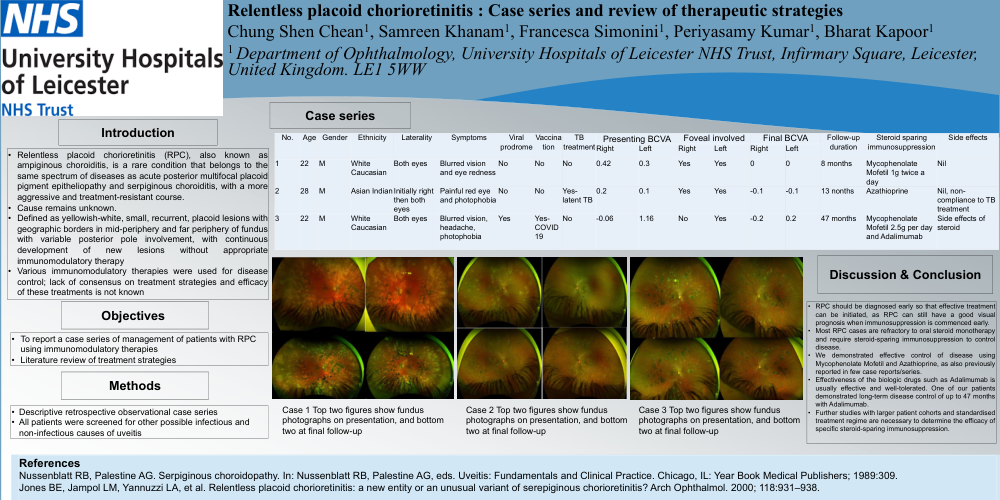
Relentless placoid chorioretinitis (RPC), also known as ampiginous choroiditis, is a rare condition that belongs to the same spectrum of diseases as acute posterior multifocal placoid pigment epitheliopathy and serpiginous choroiditis, with a more aggressive and treatment-resistant course. Cause remains unknown. Defined as yellowish-white, small, recurrent, placoid lesions with geographic borders in mid-periphery and far periphery of fundus with variable posterior pole involvement, with continuous development of new lesions without appropriate immunomodulatory therapy. Various immunomodulatory therapies were used for disease control; lack of consensus on treatment strategies and efficacy of these treatments is not known
Objectives:
• To report a case series of management of patients with RPC using immunomodulatory therapies
• Literature review of treatment strategies
Methods:
• Descriptive retrospective observational case series • All patients were screened for other possible infectious and non-infectious causes of uveitis
Discussion & Conclusion:
• RPC should be diagnosed early so that effective treatment
can be initiated, as RPC can still have a good visual
prognosis when immunosuppression is commenced early.
• Most RPC cases are refractory to oral steroid monotherapy
and require steroid-sparing immunosuppression to control
disease.
• We demonstrated effective control of disease using
Mycophenolate Mofetil and Azathioprine, as also previously
reported in few case reports/series.
• Effectiveness of the biologic drugs such as Adalimumab is
usually effective and well-tolerated. One of our patients
demonstrated long-term disease control of up to 47 months
with Adalimumab.
• Further studies with larger patient cohorts and standardised
treatment regime are necessary to determine the efficacy of
specific steroid-sparing immunosuppression.