358 posters, 97 topics, 122 sessions, 958 authors, 239 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
79th PostGraduate Assembly in Anesthesiology 2025
December 12 - 15, 2025 | New York City

2191
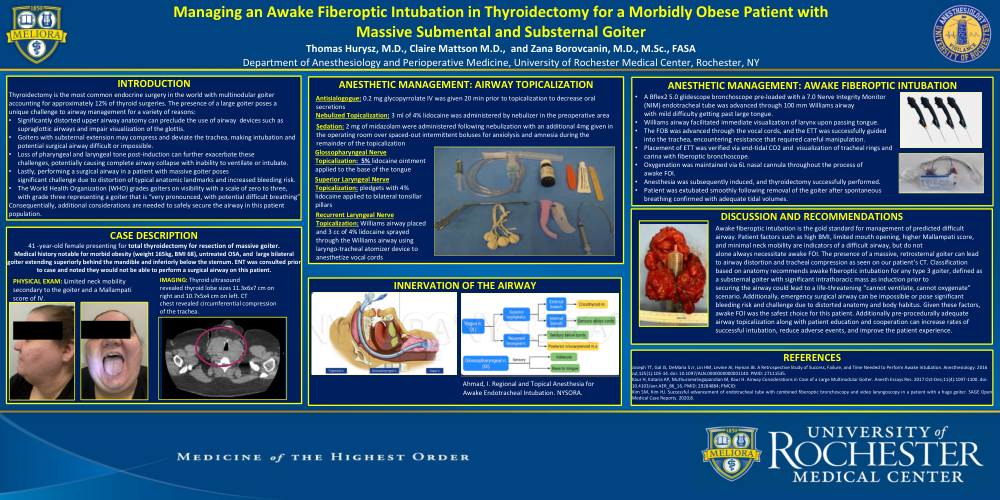
Managing an Awake Fiberoptic Intubation in Thyroidectomy for a Morbidly Obese Patient with Massive Submental and Substernal Goiter
Poster Presenter
Part of Topic
Airway
Managing an Awake Fiberoptic Intubation in Thyroidectomy for a Morbidly Obese Patient with
Massive Submental and Substernal Goiter
Thomas Hurysz, M.D., Claire Mattson M.D., and Zana Borovcanin, M.D., M.Sc., FASA
Department of Anesthesiology and Perioperative Medicine, University of Rochester Medical Center, Rochester, NY
INTRODUCTION
Thyroidectomy is the most common endocrine surgery in the world with multinodular goiter
accounting for approximately 12% of thyroid surgeries. The presence of a large goiter poses a
unique challenge to airway management for a variety of reasons:
• Significantly distorted upper airway anatomy can preclude the use of airway devices such as
supraglottic airways and impair visualization of the glottis.
• Goiters with substernal extension may compress and deviate the trachea, making intubation and
potential surgical airway difficult or impossible.
• Loss of pharyngeal and laryngeal tone post-induction can further exacerbate these
challenges, potentially causing complete airway collapse with inability to ventilate or intubate.
• Lastly, performing a surgical airway in a patient with massive goiter poses
significant challenge due to distortion of typical anatomic landmarks and increased bleeding risk.
• The World Health Organization (WHO) grades goiters on visibility with a scale of zero to three,
with grade three representing a goiter that is “very pronounced, with potential difficult breathing”
Consequentially, additional considerations are needed to safely secure the airway in this patient
population.
CASE DESCRIPTION
41 -year-old female presenting for total thyroidectomy for resection of massive goiter.
Medical history notable for morbid obesity (weight 165kg, BMI 68), untreated OSA, and large bilateral
goiter extending superiorly behind the mandible and inferiorly below the sternum. ENT was consulted prior
to case and noted they would not be able to perform a surgical airway on this patient.
IMAGING: Thyroid ultrasound
revealed thyroid lobe sizes 11.3x6x7 cm on
right and 10.7x5x4 cm on left. CT
chest revealed circumferential compression
of the trachea.
PHYSICAL EXAM: Limited neck mobility
secondary to the goiter and a Mallampati
score of IV.
Anesthetic Management: Airway Topicalization
Antisialogogue: 0.2 mg glycopyrrolate IV was given 20 min prior to topicalization to decrease oral
secretions
Nebulized Topicalization: 3 ml of 4% lidocaine was administered by nebulizer in the preoperative area
Glossopharyngeal Nerve
Sedation: 2 mg of midazolam were administered following nebulization with an additional 4mg given in
the operating room over spaced-out intermittent boluses for anxiolysis and amnesia during the
remainder of the topicalization
Topicalization: 5% lidocaine ointment
applied to the base of the tongue
Superior Laryngeal Nerve
Topicalization: pledgets with 4%
lidocaine applied to bilateral tonsillar
pillars
Recurrent Laryngeal Nerve
Topicalization: Williams airway placed
and 3 cc of 4% lidocaine sprayed
through the Williams airway using
laryngo-tracheal atomizer device to
anesthetize vocal cords
Anesthetic Management: Awake Fiberoptic Intubation
• A Bflex2 5.0 glidescope bronchoscope pre-loaded with a 7.0 Nerve Integrity Monitor
(NIM) endotracheal tube was advanced through 100 mm Williams airway
with mild difficulty getting past large tongue.
• Williams airway facilitated immediate visualization of larynx upon passing tongue.
• The FOB was advanced through the vocal cords, and the ETT was successfully guided
into the trachea, encountering resistance that required careful manipulation.
• Placement of ETT was verified via end-tidal CO2 and visualization of tracheal rings and
carina with fiberoptic bronchoscope.
• Oxygenation was maintained via 6L nasal cannula throughout the process of
awake FOI.
• Anesthesia was subsequently induced, and thyroidectomy successfully performed.
• Patient was extubated smoothly following removal of the goiter after spontaneous
breathing confirmed with adequate tidal volumes.
Discussion and Recommendations
Awake fiberoptic intubation is the gold standard for management of predicted difficult
airway. Patient factors such as high BMI, limited mouth opening, higher Mallampati score,
and minimal neck mobility are indicators of a difficult airway, but do not
alone always necessitate awake FOI. The presence of a massive, retrosternal goiter can lead
to airway distortion and tracheal compression as seen on our patient’s CT. Classification
based on anatomy recommends awake fiberoptic intubation for any type 3 goiter, defined as
a substernal goiter with significant intrathoracic mass as induction prior to
securing the airway could lead to a life-threatening “cannot ventilate, cannot oxygenate”
scenario. Additionally, emergency surgical airway can be impossible or pose significant
bleeding risk and challenge due to distorted anatomy and body habitus. Given these factors,
awake FOI was the safest choice for this patient. Additionally pre-procedurally adequate
airway topicalization along with patient education and cooperation can increase rates of
successful intubation, reduce adverse events, and improve the patient experience.