150 posters, 16 sessions, 294 authors, 70 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
Obstetric Anaesthesia Annual Scientific Meeting 2024
Thursday 9 - Friday 10 May 2024, Birmingham

6299138
Where are the tumours? Caesarean section in Von Hippel-Lindau Syndrome
Poster Presenter
Part of Topic
Where Are the Tumours? Caesarean Section in Von Hippel-Lindau Syndrome
Dr Z Majid, Dr D Hillier, Dr C Jennings, Dr M Howes
Department of Anaesthetics, Sandwell & West Birmingham Hospitals NHS Trust
INTRODUCTION
•A patient with a rare genetic condition that had implications for an anaesthetic presented for a caesarean section (CS).
•Social issues led to limited availability of information.
•Careful thought and discussion for a safe plan was crucial in providing perioperative care.
•Importance of team-work, peri-operative planning and applying holistic thinking in a time pressured scenario is highlighted.
WHAT IS VHL?
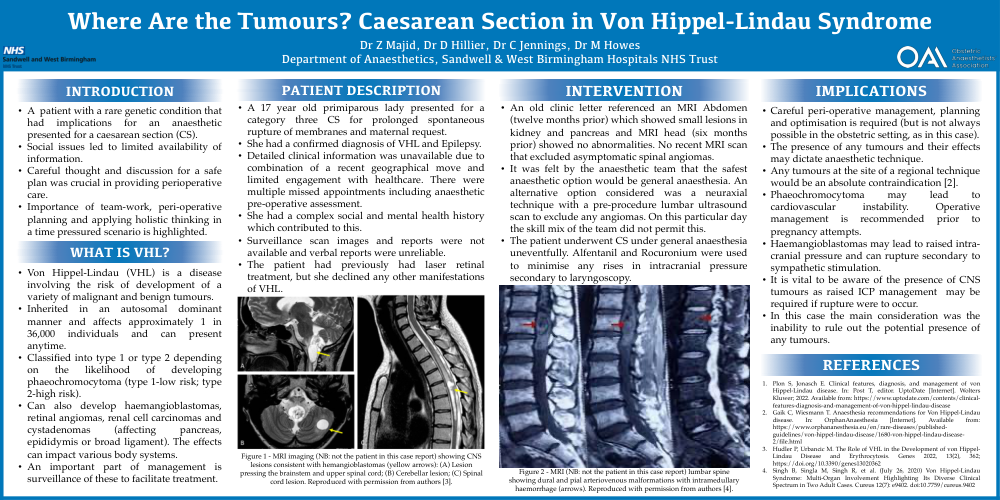
•Von Hippel-Lindau (VHL) is a disease involving the risk of development of a variety of malignant and benign tumours.
•Inherited in an autosomal dominant manner and affects approximately 1 in 36,000 individuals and can present anytime.
•Classified into type 1 or type 2 depending on the likelihood of developing phaeochromocytoma (type 1-low risk; type 2-high risk).
•Can also develop haemangioblastomas, retinal angiomas, renal cell carcinomas and cystadenomas (affecting pancreas, epididymis or broad ligament). The effects can impact various body systems.
•An important part of management is surveillance of these to facilitate treatment.
PATIENT DESCRIPTION
•A 17 year old primiparous lady presented for a category three CS for prolonged spontaneous rupture of membranes and maternal request.
•She had a confirmed diagnosis of VHL and Epilepsy.
•Detailed clinical information was unavailable due to combination of a recent geographical move and limited engagement with healthcare. There were multiple missed appointments including anaesthetic pre-operative assessment.
•She had a complex social and mental health history which contributed to this.
•Surveillance scan images and reports were not available and verbal reports were unreliable.
•The patient had previously had laser retinal treatment, but she declined any other manifestations of VHL.
INTERVENTION
•An old clinic letter referenced an MRI Abdomen (twelve months prior) which showed small lesions in kidney and pancreas and MRI head (six months prior) showed no abnormalities. No recent MRI scan that excluded asymptomatic spinal angiomas.
•It was felt by the anaesthetic team that the safest anaesthetic option would be general anaesthesia. An alternative option considered was a neuraxial technique with a pre-procedure lumbar ultrasound scan to exclude any angiomas. On this particular day the skill mix of the team did not permit this.
•The patient underwent CS under general anaesthesia uneventfully. Alfentanil and Rocuronium were used to minimise any rises in intracranial pressure secondary to laryngoscopy.
IMPLICATIONS
•Careful peri-operative management, planning and optimisation is required (but is not always possible in the obstetric setting, as in this case).
•The presence of any tumours and their effects may dictate anaesthetic technique.
•Any tumours at the site of a regional technique would be an absolute contraindication [2].
•Phaeochromocytoma may lead to cardiovascular instability. Operative management is recommended prior to pregnancy attempts.
•Haemangioblastomas may lead to raised intra-cranial pressure and can rupture secondary to sympathetic stimulation.
•It is vital to be aware of the presence of CNS tumours as raised ICP management may be required if rupture were to occur.
•In this case the main consideration was the inability to rule out the potential presence of any tumours.
REFERENCES
1.Plon S, Jonasch E. Clinical features, diagnosis, and management of von Hippel-Lindau disease. In: Post T, editor. UptoDate [Internet]. Wolters Kluwer; 2022. Available from: https://www.uptodate.com/contents/clinical-features-diagnosis-and-management-of-von-hippel-lindau-disease
2.Gaik C, Wiesmann T. Anaesthesia recommendations for Von Hippel-Lindau disease. In: OrphanAnaesthesia [Internet]. Available from: https://www.orphananesthesia.eu/en/rare-diseases/published-guidelines/von-hippel-lindau-disease/1680-von-hippel-lindau-disease-2/file.html
3.Hudler P, Urbancic M. The Role of VHL in the Development of von Hippel-Lindau Disease and Erythrocytosis. Genes 2022, 13(2), 362; https://doi.org/10.3390/genes13020362
4.Singh B, Singla M, Singh R, et al. (July 26, 2020) Von Hippel-Lindau Syndrome: Multi-Organ Involvement Highlighting Its Diverse Clinical Spectrum in Two Adult Cases. Cureus 12(7): e9402. doi:10.7759/cureus.9402