206 posters, 13 topics, 5 sessions, 713 authors, 293 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
AAPS 104th Annual Meeting
May 2-5, 2026 | Lihue, HI

D5
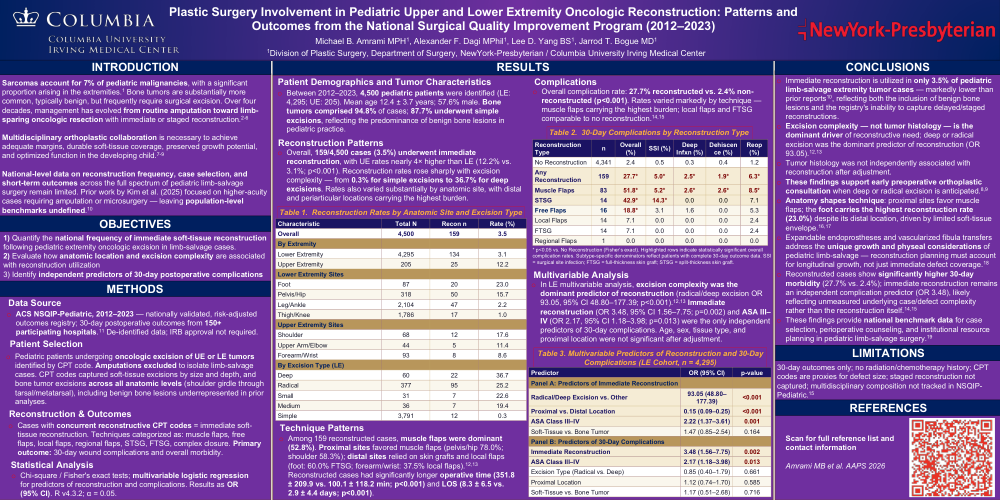
Plastic Surgery Involvement In Pediatric Upper And Lower Extremity Oncologic Reconstruction: Patterns And Outcomes From The National Surgical Quality Improvement Program (2012-2023)
Poster Presenter
Part of Topic
Craniofacial/Peds
TITLE
Plastic Surgery Involvement in Pediatric Upper and Lower Extremity Oncologic Reconstruction: Patterns and Outcomes from the National Surgical Quality Improvement Program (2012–2023)
Michael B. Amrami MPH1, Alexander F. Dagi MPhil1, Lee D. Yang BS1, Jarrod T. Bogue MD1
1Division of Plastic Surgery, Department of Surgery, NewYork-Presbyterian / Columbia University Irving Medical Center
INTRODUCTION
Sarcomas account for 7% of pediatric malignancies, with a significant proportion arising in the extremities.1 Bone tumors are substantially more common, typically benign, but frequently require surgical excision. Over four decades, management has evolved from routine amputation toward limb-sparing oncologic resection with immediate or staged reconstruction.2-6
Multidisciplinary orthoplastic collaboration is necessary to achieve adequate margins, durable soft-tissue coverage, preserved growth potential, and optimized function in the developing child.7-9
National-level data on reconstruction frequency, case selection, and short-term outcomes across the full spectrum of pediatric limb-salvage surgery remain limited. Prior work by Kim et al. (2025) focused on higher-acuity cases requiring amputation or microsurgery — leaving population-level benchmarks undefined.10
OBJECTIVES
1) Quantify the national frequency of immediate soft-tissue reconstruction following pediatric extremity oncologic excision in limb-salvage cases.
2) Evaluate how anatomic location and excision complexity are associated with reconstruction utilization
3) Identify independent predictors of 30-day postoperative complications
METHODS
Data Source
Patient Selection
Reconstruction & Outcomes
Statistical Analysis
Patient Demographics and Tumor Characteristics
Reconstruction Patterns
Technique Patterns
Complications
Multivariable Analysis
CONCLUSIONS
LIMITATIONS
30-day outcomes only; no radiation/chemotherapy history; CPT codes are proxies for defect size; staged reconstruction not captured; multidisciplinary composition not tracked in NSQIP-Pediatric.15
REFERENCES
-
American Cancer Society. Key statistics for soft tissue sarcomas. American Cancer Society website. 2025. Available at:https://www.cancer.org/cancer/types/soft-tissue-sarcoma/about/key-statistics.html. Accessed [April 5, 2026].
-
Zastrow RK, El Sayed M, LiBrizzi CL, et al. Progressive improvement in 5-year survival rates for extremity soft tissue sarcomas from 1999 to 2019. Sarcoma. 2024;2024:8880609.
-
Koulaxouzidis G, Simunovic F, Bannasch H. Soft tissue sarcomas of the arm: oncosurgical and reconstructive principles within a multimodal, interdisciplinary setting. Front Surg. 2016;3:12.
-
Rosenberg SA, Tepper J, Glatstein E, et al. The treatment of soft-tissue sarcomas of the extremities: prospective randomized evaluations of (1) limb-sparing surgery plus radiation therapy compared with amputation and (2) the role of adjuvant chemotherapy. Ann Surg. 1982;196:305–315.
-
Keus RB, Rutgers EJ, Ho GH, et al. Limb-sparing therapy of extremity soft tissue sarcomas: treatment outcome and long-term functional results. Eur J Cancer. 1994;30A:1459–1463.
-
Azoury SC, Stranix JT, Kovach SJ, et al. Principles of orthoplastic surgery for lower extremity reconstruction: why is this important? J Reconstr Microsurg. 2021;37:42–50.
-
Levin LS. The reconstructive ladder: an orthoplastic approach. Orthop Clin North Am. 1993;24:393–409.
-
Hoyt BW, Wade SM, Harrington CJ, et al. Institutional experience and orthoplastic collaboration associated with improved flap-based limb salvage outcomes. Clin Orthop Relat Res. 2021;479:2388–2396.
-
Dagi AF, Amrami MB, Gangoli NA, et al. Orthoplastic surgery research: three decades of growth and future directions. JPRAS Open. 2025;43:506–509.
-
Kim DK, Gu K, Rohde CH, et al. Reconstructive approaches to oncologic upper and lower extremity resection in pediatric populations: a retrospective NSQIP-P analysis of 428 patients. J Plast Reconstr Aesthet Surg. 2025;213:100–101.
-
American College of Surgeons. ACS NSQIP participant use data files (2009–2022). American College of Surgeons website. 2023. Available at:https://www.facs.org/quality-programs/data-and-registries/acs-nsqip/. Accessed [April 5, 2026].
-
Stiles ZE, Lohman RF, Mann GN. Plastic surgery reconstruction of sarcoma resection defects: form and function. Surg Clin North Am. 2022;102:583–599.
-
Parikh RP, Sacks JM. Lower extremity reconstruction after soft tissue sarcoma resection. Clin Plast Surg. 2021;48:307–319.
-
Slump J, Ferguson PC, Wunder JS, et al. Patient, tumour and treatment factors affect complication rates in soft tissue sarcoma flap reconstruction in a synergistic manner. Eur J Surg Oncol. 2017;43:1126–1133.
-
Chang EI, Nguyen AT, Hughes JK, et al. Optimization of free-flap limb salvage and maximizing function and quality of life following oncologic resection: 12-year experience. Ann Surg Oncol. 2016;23:1036–1043.
-
Piper M, Irwin C, Sbitany H. Pediatric lower extremity sarcoma reconstruction: a review of limb salvage procedures and outcomes. J Plast Reconstr Aesthet Surg. 2016;69:91–96.
-
Ruiz-Moya A, Lagares-Borrego A, Sicilia-Castro D, et al. Pediatric extremity bone sarcoma reconstruction with the vascularized fibula flap: observational study assessing long-term functional outcomes, complications, and survival. J Plast Reconstr Aesthet Surg. 2019;72:1887–1899.
-
Morrison SG, Binite OT, Donnan LT. Endoprosthetic use in pediatric and adolescent lower limb sarcoma treatment. J Am Acad Orthop Surg. 2026;34:e636–e647.
-
Augustine HFM, Hu J, Najarali Z, et al. Scoping review of the National Surgical Quality Improvement Program in plastic surgery research. Plast Surg (Oakv). 2019;27:54–65.
***
Contact information
Name: Michael Amrami
Email: mba2159@cumc.columbia.edu
Medical School: Columbia University Vagelos College of Physicians and Surgeons, 630 W 168th St, New York, NY 10032