1,267 posters, 47 videos, 13 topics, 4 sessions, 853 authors
ePostersLive by SciGen Technologies S.A. All rights reserved.
SOHO 2026 Annual Meeting
September 9 - 12, 2026 | George R. Brown Convention Center, Houston, Texas

MPN - 1090
Real-World Patient Characteristics, Treatment Patterns, and Blood Counts of Patients With Essential Thrombocythemia Treated With Ropeginterferon Alfa-2b in the US Community Oncology Setting
Poster Presenter
Authors
Part of Topic
Myeloproliferative Neoplasms (MPN)
Real-World Patient Characteristics, Treatment Patterns and Blood Counts of Patients with Essential Thrombocythemia Treated with Ropeginterferon Alfa-2b in the US Community Oncology Setting
Luke Fletcher1, Priya Rudolph2, Andrew J. Osterland3, Malcolm Charles3, Matthew Whitesell3, Shinya Imada4, Shaoyu Chang5, Albert Qin5, Ira Zackon3, Solly Chedid6
Background
Ropeginterferon (alfa‑2b) was FDA-approved for the treatment of polycythemia vera in November 2021.
In patients with high-risk essential thrombocythemia (ET) with inadequate response or intolerance to frontline cytoreductive therapy (1L), ropeginterferon is recommended based on promising clinical trial results:1
However, it remains unclear how ropeginterferon is utilized in real-world community oncology settings.
Objective
To describe real-world utilization of ropeginterferon for ET in the US community oncology setting.
Conclusions
Ropeginterferon was largely initiated after 1L but was also observed as 1L for younger patients. Platelets and response rates trended towards optimal levels regardless of cytoreductive therapy history.
Key Takeaways
This analysis provides preliminary insights into the real-world use and outcomes of ropeginterferon in patients with ET.
Methods
This retrospective cohort study using structured electronic health record data from The US Oncology Network or non-Network practices.
Patients were included in the study if they:
Demographics and clinical characteristics were assessed from 1L initiation, overall, and by treatment history prior to ropeginterferon (1L, 2L+).
Platelets (Plt) and white blood cells (WBC) were evaluated in patients with available data using the closest result within 60 days before ropeginterferon initiation, and at 6, 12, 18, 24 months (±60 days) after.
Complete blood count (CBC) control (at baseline) or response (at 6, 12, 18, 24 months follow-up) were defined as Plt ≤400 ×10⁹/L and WBC ≤10 ×10⁹/L at the respective timepoints.
Results
Patient Characteristics
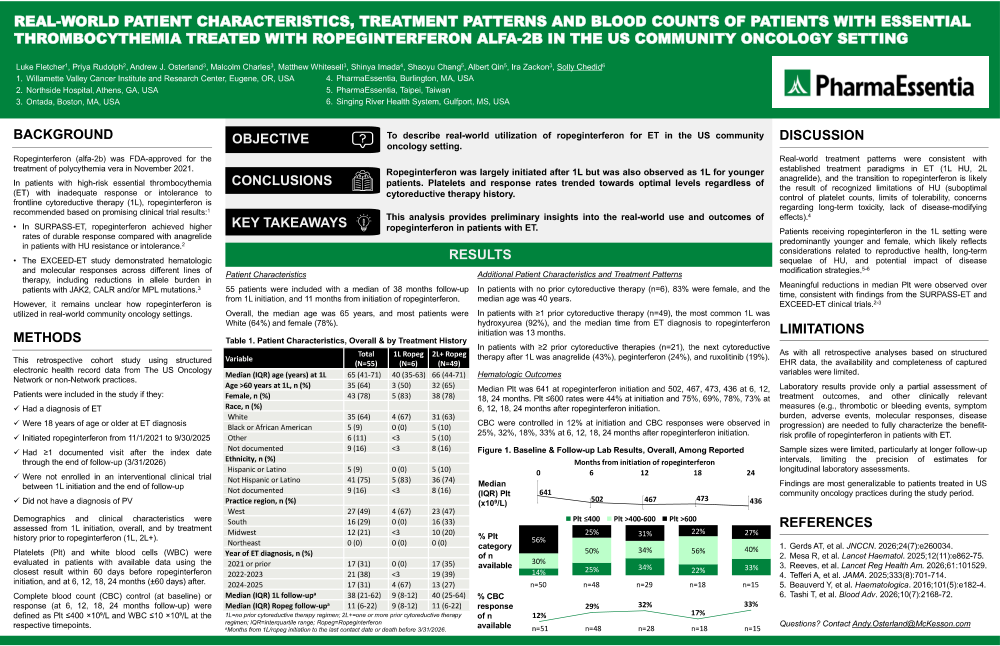
55 patients were included with a median of 38 months follow-up from 1L initiation, and 11 months from initiation of ropeginterferon.
Overall, the median age was 65 years, and most patients were White (64%) and female (78%).
Additional Patient Characteristics and Treatment Patterns
In patients with no prior cytoreductive therapy (n=6), 83% were female, and the median age was 40 years.
In patients with ≥1 prior cytoreductive therapy (n=49), the most common 1L was hydroxyurea (92%), and the median time from ET diagnosis to ropeginterferon initiation was 13 months.
In patients with ≥2 prior cytoreductive therapies (n=21), the next cytoreductive therapy after 1L was anagrelide (43%), peginterferon (24%), and ruxolitinib (19%).
Hematologic Outcomes
Median Plt was 641 at ropeginterferon initiation and 502, 467, 473, 436 at 6, 12, 18, 24 months. Plt ≤600 rates were 44% at initiation and 75%, 69%, 78%, 73% at 6, 12, 18, 24 months after ropeginterferon initiation.
CBC were controlled in 12% at initiation and CBC responses were observed in 25%, 32%, 18%, 33% at 6, 12, 18, 24 months after ropeginterferon initiation.
Discussion
Real-world treatment patterns were consistent with established treatment paradigms in ET (1L HU, 2L anagrelide), and the transition to ropeginterferon is likely the result of recognized limitations of HU (suboptimal control of platelet counts, limits of tolerability, concerns regarding long-term toxicity, lack of disease-modifying effects).4
Patients receiving ropeginterferon in the 1L setting were predominantly younger and female, which likely reflects considerations related to reproductive health, long-term sequelae of HU, and potential impact of disease modification strategies.5-6
Meaningful reductions in median Plt were observed over time, consistent with findings from the SURPASS-ET and EXCEED-ET clinical trials.2-3
Limitations
As with all retrospective analyses based on structured EHR data, the availability and completeness of captured variables were limited.
Laboratory results provide only a partial assessment of treatment outcomes, and other clinically relevant measures (e.g., thrombotic or bleeding events, symptom burden, adverse events, molecular responses, disease progression) are needed to fully characterize the benefit-risk profile of ropeginterferon in patients with ET.
Sample sizes were limited, particularly at longer follow-up intervals, limiting the precision of estimates for longitudinal laboratory assessments.
Findings are most generalizable to patients treated in US community oncology practices during the study period.
References