516 posters, 59 topics, 63 sessions, 1,127 authors, 352 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2341895
Obstetric Anesthesiology at the Forefront: Management of Submassive Saddle Pulmonary Embolism for Safe Vaginal Delivery
Part of Topic
Coagulopathy: Congenital and Iatrogenic
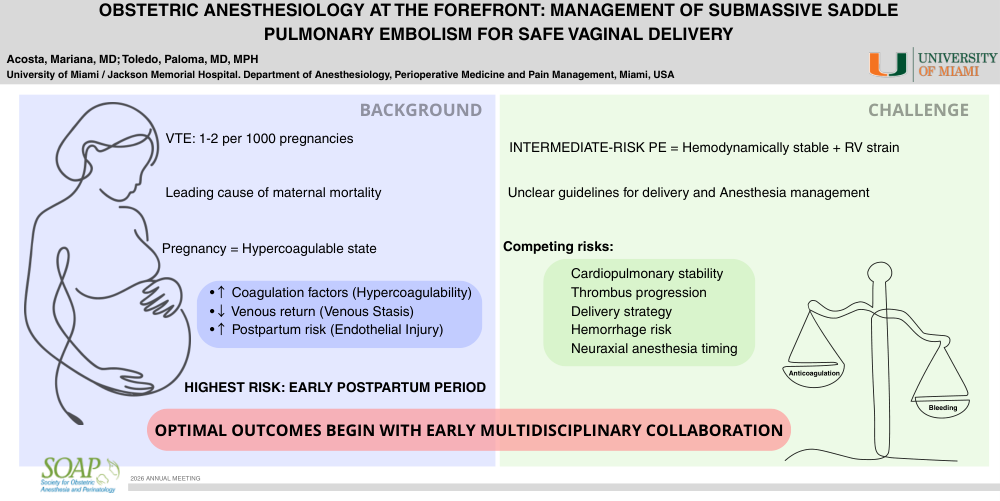
OBSTETRIC ANESTHESIOLOGY AT THE FOREFRONT: MANAGEMENT OF SUBMASSIVE SADDLE PULMONARY EMBOLISM FOR SAFE VAGINAL DELIVERY
The management of submassive saddle pulmonary embolism (PE) during pregnancy involves considerable risk and is not guided by well-established protocols. Obstetric anesthesiologists are required to synthesize expertise in cardiopulmonary physiology, anticoagulation, and neuraxial anesthesia to formulate comprehensive delivery strategies.
A 30-year-old G2P1001 at 38 weeks’ gestation with heterozygous prothrombin mutation and decreased protein S levels presented with acute dyspnea after discontinuation of prophylactic enoxaparin 48 hours earlier. She remained hemodynamically stable. CT angiography and echocardiography revealed a saddle pulmonary embolism with bilateral segmental and subsegmental involvement, right ventricular (RV) strain, and moderately reduced systolic function. Lower extremity ultrasound identified a right popliteal deep vein thrombosis (DVT). Therapeutic unfractionated heparin infusion was initiated.
A multidisciplinary team considered several high-risk management options, including emergent cesarean delivery with open thrombectomy, VA-ECMO-supported cesarean, and perimortem cesarean delivery. After 72 hours of therapeutic anticoagulation, RV function normalized. Serial imaging revealed progression of the deep vein thrombosis to an occlusive thrombus, while the pulmonary embolism burden remained unchanged. Given the extent of thrombosis, a suprarenal inferior vena cava (IVC) filter was placed. Labor was induced at 40 weeks, and labor analgesia was initiated with a DPE technique. Subcutaneous heparin was administered intrapartum until delivery and anticoagulation management adhered to ASRA and SOAP guidelines. The patient underwent an uncomplicated vaginal delivery under neuraxial anesthesia. Six hours after delivery, a continuous heparin infusion was initiated and the patient remained on labor and delivery postpartum for surveillance.
Twenty-four hours postpartum, anticoagulation was held for removal of the IVC filter. The patient experienced acute decompensation with echocardiographic evidence of right ventricular strain. Urgent mechanical thrombectomy was performed, resulting in complete recovery.
Discussion
This case highlights the essential role of obstetric anesthesiology in the multidisciplinary management of submassive saddle pulmonary embolism during pregnancy. Careful risk stratification, coordinated anticoagulation, and individualized anesthetic planning enabled safe vaginal delivery while minimizing maternal risk. The case also emphasizes the need for close postpartum surveillance, as thromboembolic risk remains high despite clinical stability. Early multidisciplinary involvement and ongoing reassessment are critical to optimizing maternal outcomes in complex pregnancy-associated thromboembolic disease.