516 posters, 59 topics, 63 sessions, 1,127 authors, 352 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
2026 SOAP Annual Meeting
April 29 - May 3, 2026 | Montreal, Quebec Canada

2341199
Management of Cesarean Delivery in a Patient with Fontan Physiology
Poster Presenter
Authors
Affiliations
Part of Topic
HEART: CONGENITAL AND VALVE CHALLENGES
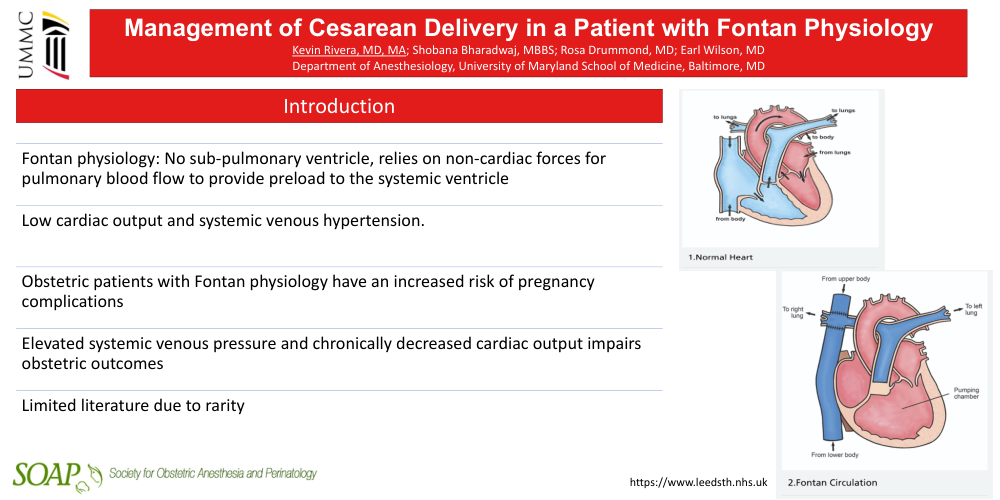
Fontan physiology: No sub-pulmonary ventricle, relies on non-cardiac forces for pulmonary blood flow to provide preload to the systemic ventricle
Low cardiac output and systemic venous hypertension.
Obstetric patients with Fontan physiology have an increased risk of pregnancy complications
Elevated systemic venous pressure and chronically decreased cardiac output impairs obstetric outcomes
Limited literature due to rarity
26yo G1P0 with a h/o double inlet left ventricle status post Fontan procedure in infancy
Vaginal delivery: gradual hemodynamic changes, better tolerated in the context of the limited preload reserve and inability to augment cardiac output that characterize Fontan physiology.
Cesarean delivery is reserved for standard obstetric indications or for patients at risk of maternal decompensation, such as acute heart failure, refractory arrhythmias, or the need for coordinated cardiovascular interventions.
Neuraxial analgesia is strongly recommended for labor as it provides effective pain control, reduces catecholamine surges, and allows for rapid conversion to surgical anesthesia if emergent cesarean delivery is required.
Maintaining preload and avoiding increases in pulmonary vascular resistance are critical in Fontan patients. Excessive fluid administration can precipitate heart failure and pulmonary edema.
Multidisciplinary planning with obstetric, cardiology, and anesthesiology teams is critical for the care of these patients.