293 posters, 56 videos, 24 topics, 13 sessions, 658 authors, 215 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
ISMICS 2025 Annual Meeting
28 - 31 May, 2025 | Istanbul, Turkey

P97
Minimally Invasive Redo Coronary Bypass Graft To The Left Anterior Descending Artery: A Novel Approach To A Hostile Sternum
Poster Presenter
Part of Topic
Video
Minimally Invasive Redo Coronary Bypass Graft To The Left Anterior Descending Artery: A Novel Approach To A Hostile Sternum
Luke J Rogers MBChB FRCS (CTh)1,2, Mohammad Reza Rezaei MD1,2, Piroze M Davierwala MD, FAHA1,2
1 Division of Cardiac Surgery, Peter Munk Cardiac Centre, Toronto General Hospital, University Health Network, Toronto, ON, Canada
2 Department of Surgery, University of Toronto, Toronto, ON, Canada
PREOPERATIVE CARE
• 71-year-old male with exertional angina (CCS III/IV)
• Prior CABG ( ̴30 years ago): LITA-LAD and Vein graft-Diagonal branch
• CV risk factors: Hypertension, Type 2 Diabetes, Prior stroke
• Transthoracic Echocardiogram: Normal biventricular function, LVID(s/d) 3.1/4.6 cm
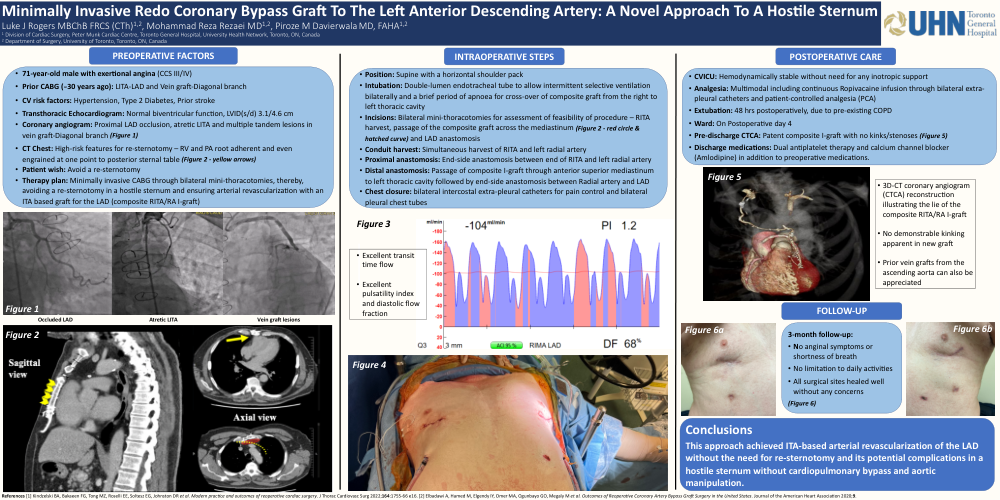
• Coronary angiogram: Proximal LAD occlusion, atretic LITA and multiple tandem lesions in vein graft-Diagonal branch (Figure 1)
• CT Chest: High-risk features for re-sternotomy – RV and PA root adherent and even engrained at one point to posterior sternal table (Figure 2 - yellow arrows
• Patient wish: Avoid a re-sternotomy
• Therapy plan: Minimally invasive CABG through bilateral mini-thoracotomies, thereby, avoiding a re-sternotomy in a hostile sternum and ensuring arterial revascularization with an ITA based graft for the LAD (composite RITA/RA I-graft)
INTRAOPERATIVE STEPS
• Position: Supine with a horizontal shoulder pack
• Intubation: Double-lumen endotracheal tube to allow intermittent selective ventilation bilaterally and a brief period of apnoea for cross-over of composite graft from the right to left thoracic cavity
• Incisions: Bilateral mini-thoracotomies for assessment of feasibility of procedure – RITA harvest, passage of the composite graft across the mediastinum (Figure 2 - red circle & hatched curve) and LAD anastomosis
• Conduit harvest: Simultaneous harvest of RITA and left radial artery
• Proximal anastomosis: End-side anastomosis between end of RITA and left radial artery
• Distal anastomosis: Passage of composite I-graft through anterior superior mediastinum to left thoracic cavity followed by end-side anastomosis between Radial artery and LAD
• Chest closure: bilateral intercostal extra-pleural catheters for pain control and bilateral pleural chest tubes
POSTOPERATIVE CARE
• CVICU: Hemodynamically stable without need for any inotropic support
• Analgesia: Multimodal including continuous Ropivacaine infusion through bilateral extra-pleural catheters and patient-controlled analgesia (PCA)
• Extubation: 48 hrs postoperatively, due to pre-existing COPD
• Ward: On Postoperative day 4
• Pre-discharge CTCA: Patent composite I-graft with no kinks/stenoses (Figure 5)
• Discharge medications: Dual antiplatelet therapy and calcium channel blocker (Amlodipine) in addition to preoperative medications.
3-month follow-up:
• No anginal symptoms or shortness of breath
• No limitation to daily activities
• All surgical sites healed well without any concerns
Conclusions
This approach achieved ITA-based arterial revascularization of the LAD without the need for re-sternotomy and its potential complications in a hostile sternum
without cardiopulmonary bypass and aortic manipulation.