372 posters, 1 audios, 13 topics, 29 sessions, 1,035 authors, 449 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
51st Annual Regional Anesthesiology and Acute Pain Medicine Meeting
April 16 - 18, 2026 | Phoenix, Arizona

2362888
Incidence of Postoperative Opioid Use Disorder Following Major Surgery
Poster Presenter
Authors
Soraya Mehdipour, Carla Marienfeld, Gregory Polston, Sesh Mudumbai, Rodney Gabriel
Affiliations
Division of Perioperative Informatics, Department of Anesthesiology, University of California San Diego, La Jolla, CA, USA., Department of Psychiatry, University of California San Diego, La Jolla, CA, USA., Department of Anesthesiology, University of California San Diego, La Jolla, CA, USA., Department of Anesthesiology, Perioperative and Pain Medicine, Stanford University School of Medicine, Palo Alto, CA, USA
Part of Topic
Late Breaking Scientific Abstracts
BACKGROUND:
The opioid crisis remains a public health emergency in the U.S. In a subset of surgical patients, perioperative opioid exposure is a pathway to persistent use and opioid use disorder (OUD). Opioid stewardship and public health programs have sought to decrease the incidence of OUD.
METHODS:
Retrospective observational study using Epic Cosmos, a de-identified EHR research platform containing 300 million patients from participating U.S. health systems.
Adult patients (≥18 years) undergoing 27 common surgical procedures identified by CPT codes between 2014–2024 were included.
Outcome: clinically documented OUD defined by ICD-10 F11 or SNOMED 75544000, occurring 90 days to 2 years postoperatively.
Postoperative OUD incidence was reported per 100,000 operations with 95% confidence intervals (CI) calculated using the Wilson score method.
Temporal trends were evaluated using linear regression of annual incidence rates, reporting slope, R², and P values.
RESULTS:
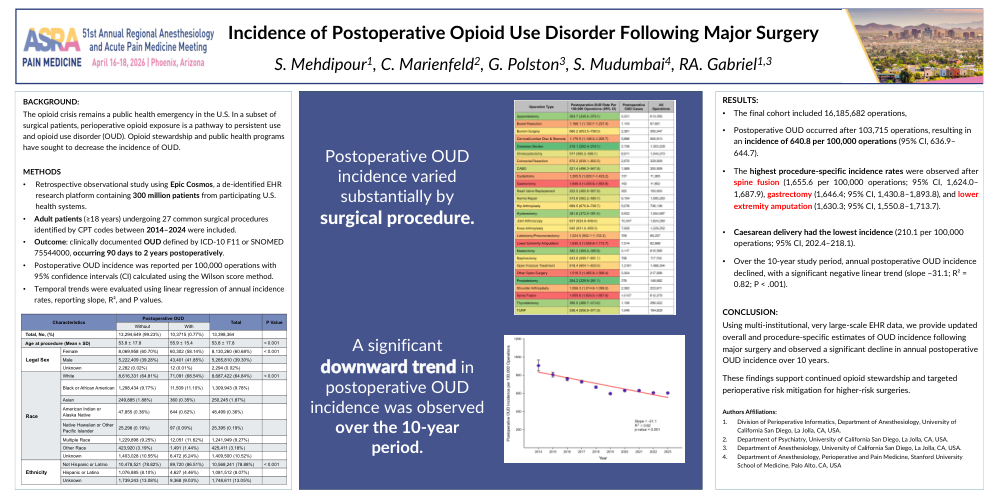
The final cohort included 16,185,682 operations,
Postoperative OUD occurred after 103,715 operations, resulting in an incidence of 640.8 per 100,000 operations (95% CI, 636.9–644.7).
The highest procedure-specific incidence rates were observed after spine fusion (1,655.6 per 100,000 operations; 95% CI, 1,624.0–1,687.9), gastrectomy (1,646.4; 95% CI, 1,430.8–1,893.8), and lower extremity amputation (1,630.3; 95% CI, 1,550.8–1,713.7).
Caesarean delivery had the lowest incidence (210.1 per 100,000 operations; 95% CI, 202.4–218.1).
Over the 10-year study period, annual postoperative OUD incidence declined, with a significant negative linear trend (slope −31.1; R² = 0.82; P < .001).
CONCLUSION:
Using multi-institutional, very large-scale EHR data, we provide updated overall and procedure-specific estimates of OUD incidence following major surgery and observed a significant decline in annual postoperative OUD incidence over 10 years.
These findings support continued opioid stewardship and targeted perioperative risk mitigation for higher-risk surgeries.