343 posters, 5 videos, 2 audios, 18 topics, 33 sessions, 263 authors, 202 institutions
ePostersLive by SciGen Technologies S.A. All rights reserved.
24th Annual Pain Medicine Meeting 2025
November 13-15, 2025| JW Marriott Austin, Austin, Texas

2196945
Thoracic Outlet Syndrome (TOS) Successfully Managed with Botulinum Toxin Injection Following Multiple Failed Surgeries
Poster Presenter
Authors
Affiliations
Part of Topic
Medically Challenging Cases
Introduction
Thoracic Outlet Syndrome (TOS) refers to a
collection of subjective symptoms and
clinical findings caused by compression of
the neurovascular bundle as it passes
through the thoracic outlet. Patients with
persistent or worsening symptoms despite
conservative management may be surgical
candidates. We report a case of a patient
with post-traumatic neurogenic thoracic
outlet syndrome with persistent pain
following multiple surgeries and neurolysis
but had significant pain relief following a
left pectoralis minor botulinum toxin
injection.
Discussion
Initial management of TOS includes physical therapy, pharmacologic agents,
and injections (anesthetic, steroid, or botulinum toxin).
Patients with persistent symptoms are candidates for thoracic outlet
decompression.
Due to recurrence and surgical complications, the benefit of surgical
intervention remains questionable.
Our patient failed multiple surgeries but had significant relief with a botulinum
toxin injection.
This highlights the potential of botulinum toxin for refractory TOS.
More research is needed to identify long-term treatment options.
Results
Our patient is a 28-year-old female with left-sided post-traumatic
neurogenic thoracic outlet syndrome following a whiplash injury. She
reported left shoulder, arm, and finger pain with weakness, numbness, and
tingling, unrelieved by physical therapy or oral medications. She
underwent left first rib resection, brachial plexus neurolysis, scalenectomy,
and pectoralis minor tenotomy with initial relief, but symptoms returned
after another motor vehicle accident. Diagnosed with recurrent pectoralis
minor syndrome, she had resection of the left pectoralis minor and repeat
neurolysis, but symptoms persisted. At our pain clinic, she presented with
pain, weakness, allodynia, and hyperalgesia of the left arm, chest wall, and
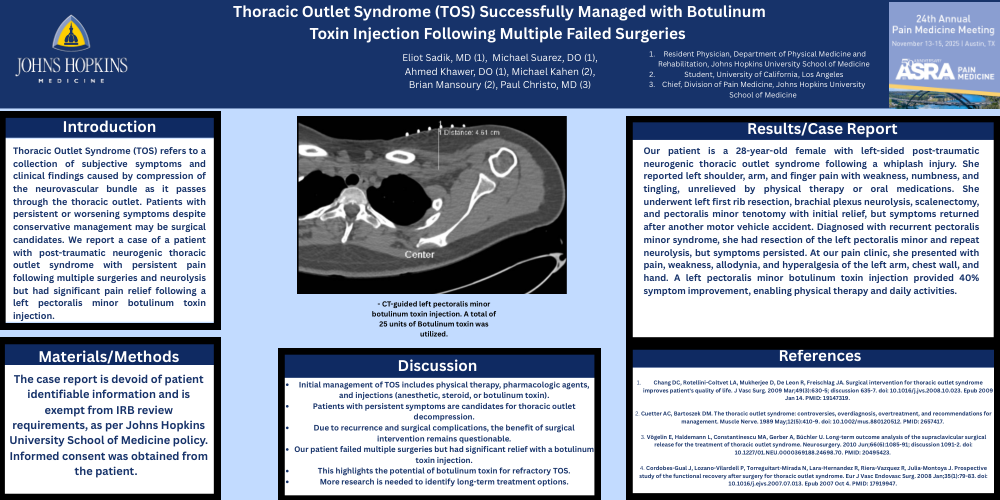
hand. A left pectoralis minor botulinum toxin injection provided 40%
symptom improvement, enabling physical therapy and daily activities.